Searching...
Can't find what you're looking for. Try different keywords.


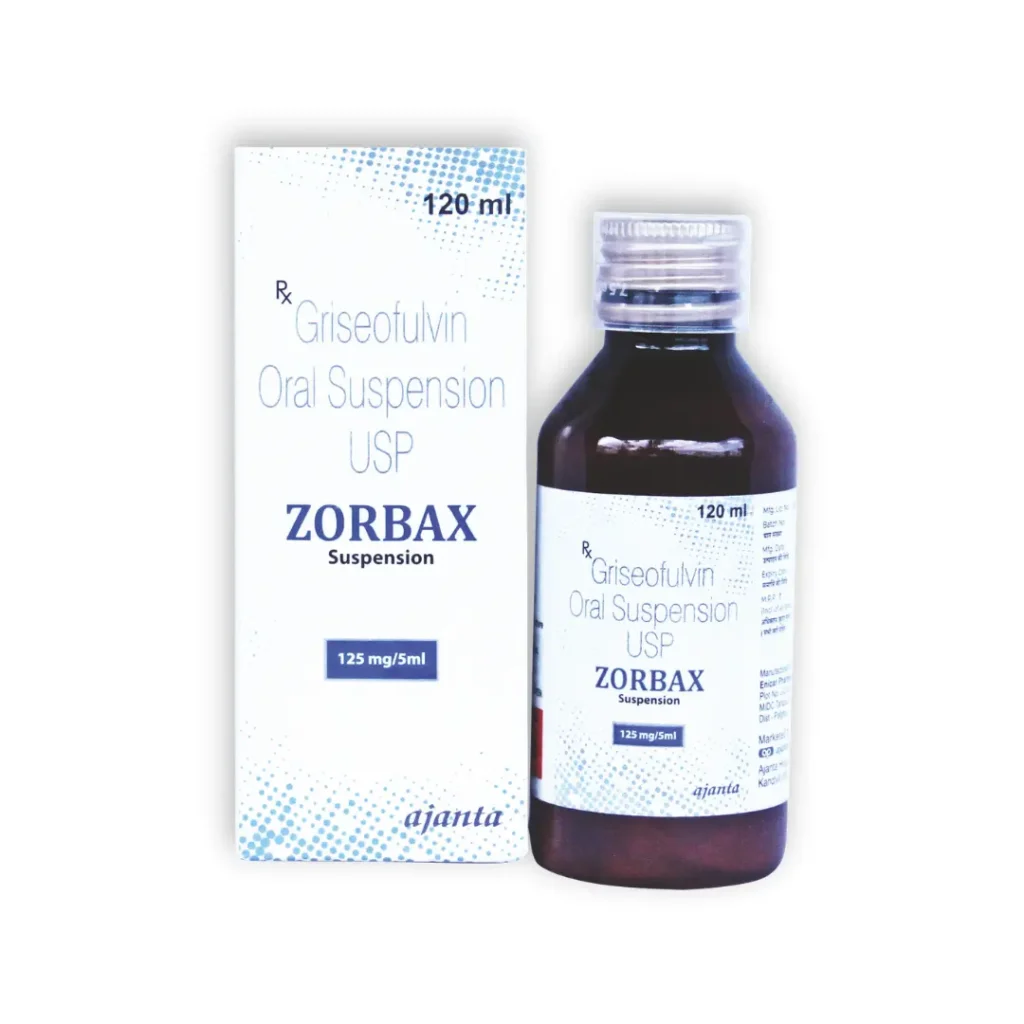

Griseofulvin
125 mg / 5ml
Zorbax Suspension is indicated for the treatment of Fungal Infections
When adverse reactions occur, they are most commonly of the hypersensitivity type such as skin rashes, urticaria, erythema multiforme-like drug reactions, and rarely, angioneurotic edema, and may necessitate withdrawal of therapy and appropriate countermeasures. Paresthesia of the hands and feet have been reported after extended therapy. Other side effects reported occasionally are oral thrush, nausea, vomiting, epigastric distress, diarrhea, headache, fatigue, dizziness, insomnia, mental confusion, and impairment of performance of routine activities. Proteinuria and leukopenia have been reported rarely.
Griseofulvin decreases the activity of warfarin-type anticoagulants so that patients receiving these drugs concomitantly may require dosage adjustment of the anticoagulant during and after griseofulvin therapy. Barbiturates usually depress griseofulvin activity and concomitant administration may require a dosage adjustment of the antifungal agent. There have been reports in the literature of possible interactions between griseofulvin and oral contraceptives. The effect of alcohol may be potentiated by griseofulvin, producing such effects as tachycardia and flush
Microbiology – Griseofulvin is fungistatic with in vitro activity against various species of Microsporum, Epidermophyton and Trichophyton. It has no effect on bacteria or other genera of fungi.
The half life of Griseofulvin in Zorbax Suspension is 9.5-21 hours
Absorption: The absorption of griseofulvin from the gastrointestinal tract is varaible and incomplete. On average, less than 50% of the oral dose is absorbed, but administration after a fatty meal, and a reduction in particle size will increase the rate and extent of the absorption. Distribution: The volume of distribution is about 0.7 L / Kg, and griseofulvin is ca 80 % bound to plasma proteins, predominantly serum albumin. Griseofulvin crosses the placenta, and may be excreted in breast milk. There is selective deposition of griseofulvin in newly formed keratin of hair, skin, and nails, which gradually moves to the surface of these appendages. Metabolism: Griseofulvin undergoes metabolism to inactive metabolites, principally 6- desmethylgriseofulvin, or its glucuronide conjugate. Excretion: The terminal plasma half life ranges from 9.5-21 hours, with considerable intersubject variability. The majority of the dose, as 6-desmethylgriseofulvin or the glucuronide conjugate, and other metabolites is excreted in the urine, with less than 1% administered dose beinge excreted as unchanged griseofulvin. The remainder of the dose, principally as metabolites, is excreted in bile and faeces. Renal insufficiency does not lead to accumulation.
Contraindicated
Contraindicated
Pediatric Use: Approximately 7.3 mg per kg of body weight per day of ultramicrosize griseofulvin is an effective dose for most pediatric patients. On this basis, the following dosage schedule is suggested: 16-27 kg: 125 mg to 187.5 mg daily. over 27 kg: 187.5 mg to 375 mg daily Children and infants 2 years of age and younger – dosage has not been established. Clinical experience with griseofulvin in children with tinea capitis indicates that a single daily dose is effective. Clinical relapse will occur if the medication is not continued until the infecting organism is eradicated.
Daily administration of 375 mg (as a single dose or in divided doses) will give a satisfactory response in most patients with tinea corporis, tinea cruris, and tinea capitis. For those fungal infections more difficult to eradicate, such as tinea pedis and tinea unguium, a divided dose of 750 mg is recommended.
Subscribe to our newsletter and be the first to receive insights, updates, and expert tips on optimizing your financial management.